Assessments of a health-related matter of interest, importance, or worry to a patient, patient’s authorized representative, or patient’s healthcare provider that could identify a need, problem, or condition.
Description (*Please confirm or update this field for the new USCDI version*)
Assessment of a patient's level of cognitive functioning. (e.g., alertness, orientation, comprehension, concentration, and immediate memory for simple commands)
Applicable Vocabulary Standard(s)
Applicable Standards (*Please confirm or update this field for the new USCDI version*)
Logical Observation Identifiers Names and Codes (LOINC®) version 2.72
Submitted By: Michelle Dougherty
/ Submitted on behalf of the CMS Data Element Library (DEL) Health IT Workgroup
Data Element Information
Data Element Description
This data element carries information on Mental Functioning that is exchanged as observations. (Observations are characteristics that can be tested, measured, or observed and are communicated with a name-value pair structure). Mental functioning is a broad domain. Using the conceptual framework of the International Classification of Function (ICF), it includes aspects such as memory functions, orientation functions, attention functions, etc.
Notes:
• This data element is constrained to health data represented in data structures for observations. Observations should be represented using terminologies supporting this conceptual model, such as LOINC, which is designed for this purpose. Representing problems, goals, and other types of information related to functioning should use other data class structures as appropriate.
• Examples of Mental function concepts can be found in the ICF browser at: https://apps.who.int/classifications/icfbrowser
• Examples of demonstrated use of Mental Function data can be found in the PACIO FHIR Cognitive Function Implementation Guide which supports exchange of observation data from PHQ-9, BIMS, CAM, MOCA, MMSE assessments coded with LOINC.
Use Case Description(s)
Use Case Description
Exchange of Data for Transitions of Care and Care Coordination:
Data exchange between acute care, post-acute care (PAC) providers, the patient and caregivers, and other care settings (physician practices, community based services, etc.), using common standards and definitions, supports patient-centered care by providing access to longitudinal information at transition and facilitating care coordination. An ASPE and CMS study found that 45% of Medicare patients required PAC services after an acute hospital stay.* The importance of exchanging data elements related to functioning at transition of care is described in the findings of the 2020 national study on hospital adoption of electronic health record functionality to support age-friendly care.** It concluded that US acute care hospital EHRs lack key features and health information exchange of important information that supports care for older adults, including structured documentation on mentation and mobility. Emerging work on frailty indices have found relationships between poor physical functioning and risk of adverse health outcomes.*** An ASPE funded project is currently exploring how health systems may use EHR-based data for frailty algorithms, including aspects of frailty related to mobility and cognitive limitations. Having functional limitations does not necessarily mean that a person is frail. Widespread exchange of the content specified in this data class (and corresponding data elements) proposal has the potential to improve patient and provider communications and supports access to longitudinal information that enables improved efficiencies, improved quality of care, and improved health outcomes.
The 2014 Improving Medicare Post-Acute Care Transformation (IMPACT) Act required the standardization and interoperability of specific categories of PAC patient assessment content, including the content applicable to the proposed data elements. For PAC settings including SNFs, HHAs, and specialty hospitals (inpatient rehabilitation facilities (IRFs), long term care hospitals (LTCH)), standardized patient assessment data reported to the Centers for Medicare and Medicaid Services (CMS) includes items about mental function, mobility, self-care and domestic life/IADLs that represented as observations. All of these concepts are represented in LOINC. The conceptual framework of the International Classification of Functioning (ICF) informed the development of these and other functioning data elements. Prior to use on the patient assessment, these data elements were tested for validity and reliability and are used for quality measurement, payment, public reporting and oversight.
Representation of functioning observations is well supported by all of the common exchange paradigms, including messages, documents, and APIs. Here we highlight the two most prevalent.
• FHIR: The HL7 PACIO project is focused on advancing interoperable health data exchange between PAC and other providers, patients, and key stakeholders across health care. The project has developed a FHIR Functional Status Implementation Guide and a FHIR Cognitive Status Implementation Guide (IG) which will be balloted as a standard for trial use in October 2020. The IG leverages the FHIR exchange structures and LOINC-coded observations. Successful exchange of functioning data from PAC assessments using the PACIO IGs was demonstrated in the January, May, and September 2020 Connectathons. PAC assessment data about mental function, mobility, self-care, and domestic life/IADLs are also included in use cases for the eLTSS and Care Plan HL7 FHIR projects.
• C-CDA: This data class and data elements are aligned with C-CDA templates for mental status and functional status. Functioning information from SNF and HHA patient assessments are being exchanged with HIEs and other providers using HL7 C-CDA. This exchange is supported by select EHR vendors, VorroConnect KeyHIE Transform, and the 360X data exchange initiative.
Sources:
*RTI International analysis of 2014 Medicare claims under contract with the Assistant secretary for Planning and Evaluation, August 2018, unpublished
**Hospital adoption of electronic health record functions to support age-friendly care: results from a national study. JAMIA 08/2020. https://pubmed.ncbi.nlm.nih.gov/32772089/
*** Validation of a Claims-Based Frailty Index Against Physician Performance and Adverse Health Outcomes in Health and Retirement Study. J Gerontol A Biol Sci Med Sci, 2019, Vol. 74, No. 8, 1271–1276
- VorroConnect: https://vorroconnect.com/products/healthcare-information-exchange/
- 360X: https://oncprojectracking.healthit.gov/wiki/display/TechLab360X/360X+Home
Estimate the breadth of applicability of the use case(s) for this data element
Stakeholder estimates can be challenging since the proposed data elements should be usable across the continuum of care, and beyond the traditional healthcare system – into the community. We know that PAC providers are required to collect standardized and interoperable data elements related to functioning at patient admission, discharge, and specified time intervals using defined CMS assessments. However, standardized capture of data elements related to functioning is inconsistent in other healthcare settings such as acute care hospitals and primary care/specialty care physician practices.
In attempting to quantify stakeholders potentially involved in the use and exchange of data elements related to functioning, we relied on the July 2020 CMS Fast Facts to provide a picture of both providers and patients (i.e., beneficiaries), albeit from a Medicare perspective. While the numbers that appear below are significant, it is important to remember that they are constrained to Medicare providers and persons served who are covered by original Medicare. Non-Medicare providers and patients who are not covered by original Medicare (e.g., Medicaid only, privately insured, etc.) are not reflected in the counts but would still be stakeholders for the proposed data elements. It is also important to note that caregivers and providers of long term supports and services (e.g., home health aides, meals on wheels) are increasingly recognized as important stakeholders in health information exchange but are also not reflected in the metrics below.
Institutional Medicare Providers (for 2019) & Persons Served (original Medicare for 2018)
• Inpatient Hospitals - 6,023 providers; 6.5 million persons served
• SNFs - 15,103 providers; 1.7 million persons served
• HHAs – 11,157 providers; 3.6 million persons served (Medicare Part A skilled and Medicare Part B non-skilled services)
Notes:
• The CMS Fast Facts reports include the 306 IRF providers and 367 LTCH providers, who are subject to CMS PAC assessment provisions, in the “inpatient hospital” counts for both providers and persons served. There is no setting specific count of persons served for these IRF and LTCH providers.
• Other types of Medicare Institutional providers were identified that would be stakeholders for data elements related to functioning, but for which separate counts of persons served were not available. There were 21,000+ providers identified as outpatient physical therapy/speech pathology, rural health clinics, federally qualified health centers, comprehensive outpatient rehab facilities, or hospice providers.
Non-institutional Medicare Providers (for 2019)
• Primary care, surgical specialties, medical specialties, and psychiatry – 537,390 providers
• Non-physician practitioners – 489,765 providers
Note:
• The non-physician practitioner classification (e.g., nurse practitioners, physician assistants) does not provide sufficient detail to discern the numbers of these practitioners associated with the targeted primary care and specialty providers.
Support Quality Measures:
Standardized and interoperable PAC functioning data elements have the potential to be utilized to support clinical quality measures (CQMs) in a variety of existing quality reporting programs and future digital quality measures.
• Mental Status: As cognitive function can impact patient safety, as well as overall physical functioning, the data elements could be used for a quality measure that is focused specifically on cognition but may also be relevant to the construct of other eCQMs. Currently, CMS149v8, Dementia: Cognitive Assessment, has been validated for use with nursing home patients only using the Minimum Data Set (MDS) Brief Interview of Mental Status (BIMS).
• Mobility, Self-care, Domestic Life/IADLs: Dependence on others for ADL assistance can lead patient’s to feelings of helplessness, isolation, diminished self-worth, and loss of control over one’s destiny. As inactivity increases, complications such as pressure ulcers, falls, contractures, depression, and muscle wasting may occur.
• Functioning data elements could be used for a quality measure that is focused specifically on this data element (e.g., MIPS CQM #282: Dementia: Functional Status Assessment), and may also be relevant to the construct of other eCQMs. The Clinical Reasoning and PACIO FHIR initiatives have used PAC data in the May and September 2020 Connectathon demonstrations of CMS149 and CMS104.
Currently, there are six NQF endorsed measures that address concepts of functioning (NQF #2631 thru 2636) and use standardized data elements related to functioning from PAC assessments. One or more of these NQF measures are a component of the CMS Quality Reporting Programs (QRPs) for SNFs, IRFs, LTCHs, and HHAs. Additionally, data related to functioning are used in quality measures that help inform facility ratings in the Five Star Quality Rating System whose results are made available on CMS public reporting websites.
Estimate the breadth of applicability of the use case(s) for this data element
Stakeholder estimates can be challenging since the proposed data elements should be usable across the continuum of care, and beyond the traditional healthcare system – into the community. We know that PAC providers are required to collect standardized and interoperable data elements related to functioning at patient admission, discharge, and specified time intervals using defined CMS assessments. However, standardized capture of data elements related to functioning is inconsistent in other healthcare settings such as acute care hospitals and primary care/specialty care physician practices.
In attempting to quantify stakeholders potentially involved in the use and exchange of data elements related to functioning, we relied on the July 2020 CMS Fast Facts to provide a picture of both providers and patients (i.e., beneficiaries), albeit from a Medicare perspective. While the numbers that appear below are significant, it is important to remember that they are constrained to Medicare providers and original Medicare persons served. Non-Medicare providers and patients who are not covered by original Medicare (e.g., Medicaid only, privately insured, etc.) are not reflected in the counts but would still be stakeholders for the proposed data elements. It is also important to note that caregivers and providers of long term supports and services (e.g., home health aides, meals on wheels) are increasingly recognized as important stakeholders in health information exchange but are also not reflected in the metrics below.
Institutional Medicare Providers (for 2019) & Persons Served (original Medicare for 2018)
• Inpatient Hospitals - 6,023 providers; 6.5 million persons served
• SNFs - 15,103 providers; 1.7 million persons served
• HHAs – 11,157 providers; 3.6 million persons served (Medicare Part A skilled and Medicare Part B non-skilled services)
Notes:
• The CMS Fast Facts reports include the 306 IRF providers and 367 LTCH providers, who are subject to CMS PAC assessment provisions, in the “inpatient hospital” counts for both providers and persons served. There is no separate count of persons served for these IRF and LTCH providers.
• Other types of Medicare Institutional providers were identified that would be stakeholders for data elements related to functioning, but for which separate counts of persons served were not available. There were a were 21,000+ providers identified as outpatient physical therapy/speech pathology, rural health clinics, federally qualified health centers, comprehensive outpatient rehab facilities, or hospice providers.
Non-institutional Medicare Providers (for 2019)
• Primary care, surgical specialties, medical specialties, and psychiatry – 537,390 providers
• Non-physician practitioners – 489,765 providers
Note:
• The non-physician practitioner classification (e.g., nurse practitioners, physician assistants) does not provide sufficient detail to discern the numbers of these practitioners associated with the targeted primary care and specialty providers.
Improving patient experience of care (quality and/or satisfaction)
Improving the health of populations
Reducing the cost of care
Improving provider experience of care
Maturity of Use and Technical Specifications for Data Element
Applicable Standard(s)
LOINC.
LOINC is a freely available global standard that contains a well-developed model for representing variables, answer lists, and the collections that contain them.* Many clinical assessments, scales, and other observations related to functioning are present in LOINC, including all of the variables on the PAC assessments for SNFs, IRFs, LTCHs, and HHAs. Regenstrief operates a robust process for adding new content (including functioning assessment instruments) if key gaps are identified.
*PMID: 22899966
PACIO Project: FHIR Cognitive Status Implementation Guide (STU ballot scheduled for October 2020)
PACIO Project: FHIR Functional Status Implementation Guide (STU ballot scheduled for October 2020)
Current Use
In limited use in test environments only
Extent of exchange
N/A
Potential Challenges
Restrictions on Standardization (e.g. proprietary code)
We are not aware of restrictions on standardization of proposed data elements in PAC settings. However, we are not aware of standardization of these proposed data elements in other care settings such as acute care hospitals, physician practices, etc.
Restrictions on Use (e.g. licensing, user fees)
Intellectual property issues related to use of the BIMS, CAM, and PHQ2/PHQ9 in PAC assessments have been addressed through appropriate annotations on printed and electronic representation of these items. as proposed data elements have not been standardized in acute care settings, assessments of functioning used in these settings would need to be evaluated for intellectual property considerations.
Privacy and Security Concerns
This data should be exchanged securely. Secure data transfer process as governed by CMS and ONC should be followed
Estimate of Overall Burden
PAC settings such as SNFs, IRFs, LTCH, and HHAs, are required to report standardized patient assessment data to CMS for purposes of Medicare payment, quality reporting, and compliance surveys. These patient assessments include concepts of mental function, mobility, self-care and domestic life/IADLs.
Outside of the post-acute care settings, these data elements may not be structured and are not captured with consistency.
Other Implementation Challenges
For PAC settings, the proposed data elements are collected from standardized assessments and reported to CMS using agency specific data submission protocols and specifications. However, as PAC providers are excluded from EHR certification requirements, there is significant variance in the adoption of interoperability terminologies and exchange standards by EHR vendors supporting post-acute care settings. Additionally, while some providers may capture mental status, mobility, self-care and/or domestic life/IADL data in acute care or outpatient settings, they may use other instruments (observations) to capture this data.
The American Occupational Therapy Association supports and appreciates the inclusion of mental functions in the health status data class. AOTA participates in the PACIO Project work on the Cognitive Status Implementation Guide that has since been renamed to Functional Performance. Developing an interoperable and interdisciplinary method of collecting information on an individual's mental functions is crucial in early detection of cognitive decline, onset of delirium, or identification of trends over time. AOTA encourages ONC to consider how this data can be efficiently and accurately collected beyond admission and discharge and how data from other clinicians, such as occupational therapy practitioners, can be utilized in this data class.
NACHC is supportive of the concept of mental function; however, it is not likely to support interoperability to solely create a terminology binding to support the concept. Because the concepts in the draft version generally represent non-semantically equivalent types of cognitive function and observations about these conditions, we believe that creating a class for this concept will likely create larger transitions of care documents without being able to be processed by receiving systems.
Furthermore, there will likely be confusion between which assessments constitute “Functional Status” and “Mental Function”. Would recommend renaming this term. This approach creates liability for providers who at best can use this data as free text in this case and contributes to data overload and burnout.
We strongly recommend providing either specific categories of functional status with equivalent semantics and clear terminology bindings.
The "Optional Background Text / Cover Letter" field provides space for additional context or introductory information related to your comment.
If you wish to provide context, explanation, or an introduction to your comment, enter this information in the field labeled "Optional Background Text / Cover Letter." This is entirely optional and is most useful when submitting multiple related comments or when additional background would help reviewers understand your feedback.
If you are only commenting on a single data class or element, you may leave this field blank.
2. Select the Data Class
To specify which data class your comment addresses:
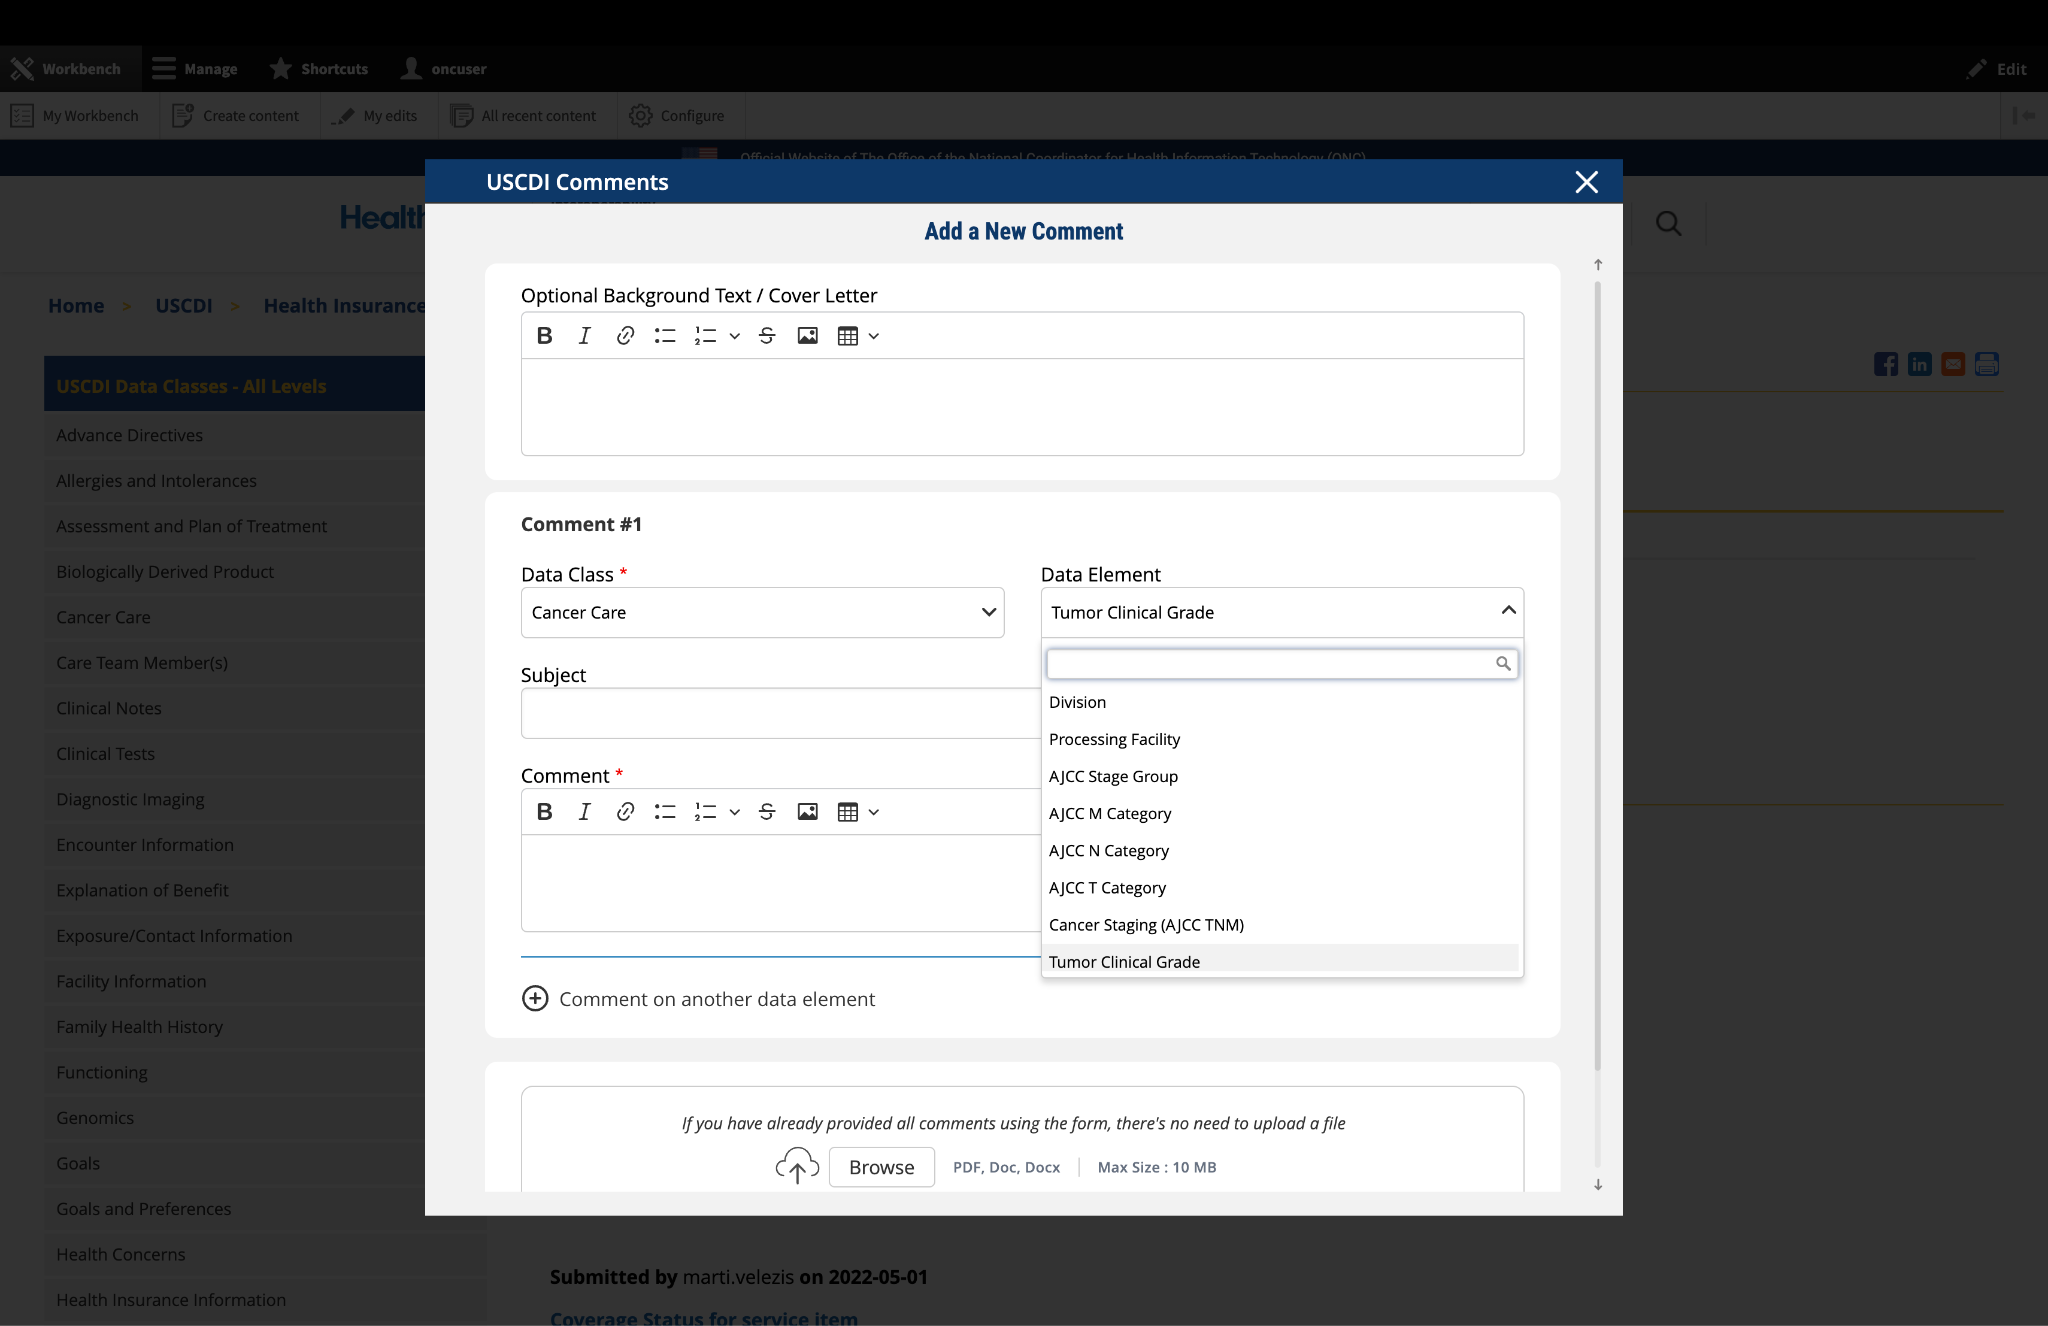
In the "Data Class" drop-down menu, select the appropriate data class you want to comment on.
If you are providing a general comment that is not specific to a data element, select "General" from the options. Comments with this designation will be displayed on the USCDI landing page.
Note that the Data Class field will automatically populate based on your current location in the platform:
If you are on a data class page, the field will be set to that specific data class
If you are on a data element page, the corresponding data class will be pre-selected
3. Select the Data Element
To specify which data element your comment addresses:
In the "Data Element" drop-down menu, select the specific data element you want to comment on.
The drop-down menu will display only the elements available under the data class you selected in the previous step.
You can use the search function within the drop-down to quickly locate a specific data element.
If you are commenting on the data class itself rather than a specific element, you may leave this field blank.
Note: Comments on a specific data element will appear on the respective data element page, while comments on a data class (without a specific element selected) will appear on the landing page for that data class.
Fig 1 The "Data Class" and "Data Element" dropdown menus allow users to specify the exact content they wish to comment on.
4. Optional: Propose New Data Class or Element
If you cannot find the appropriate data class or element for your comment:
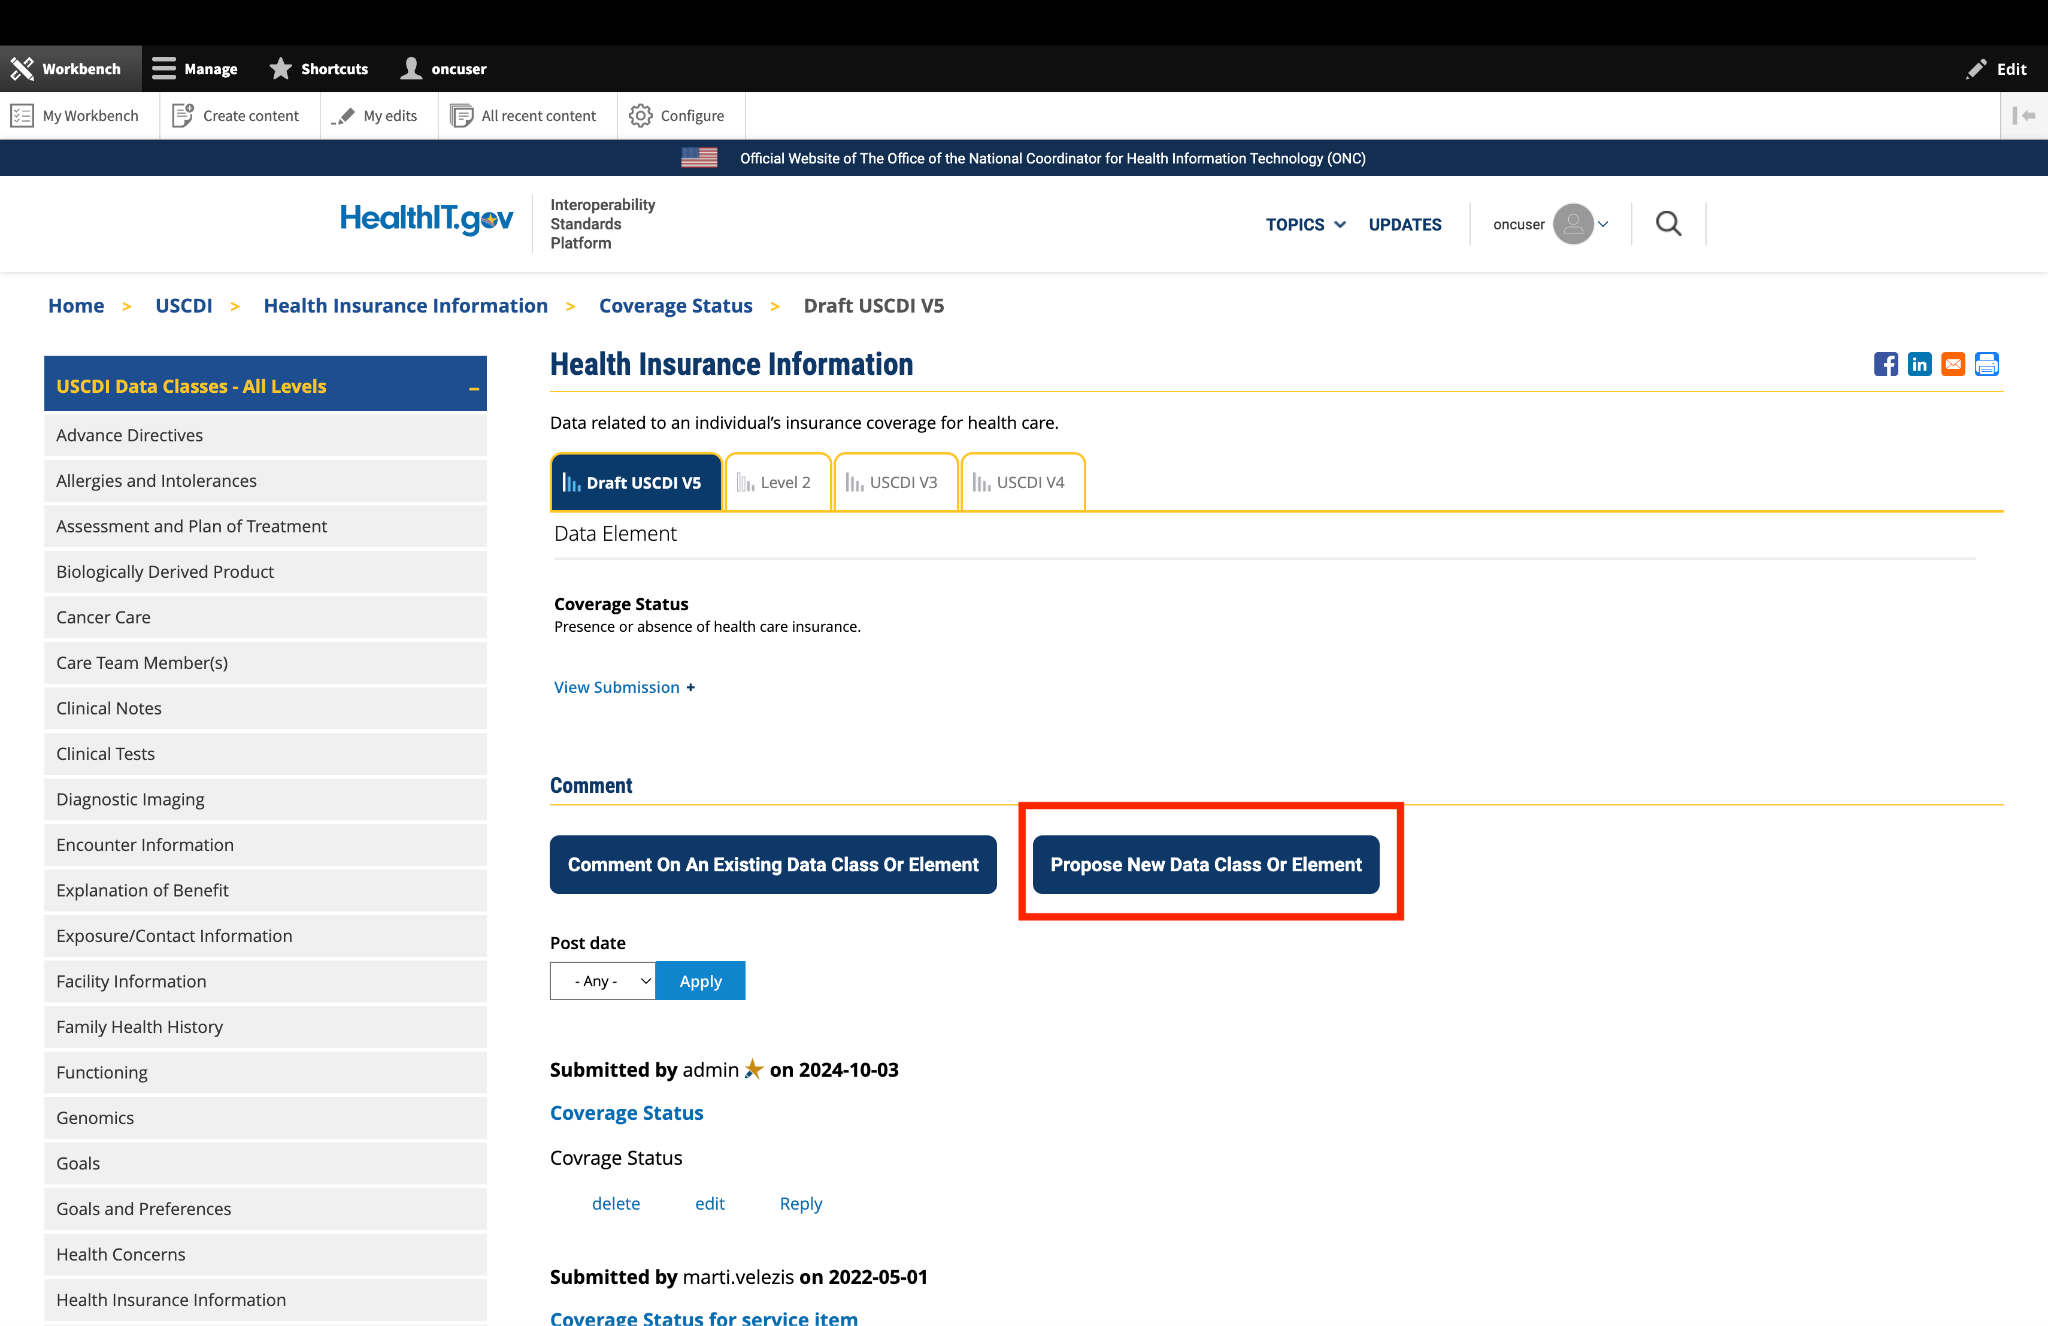
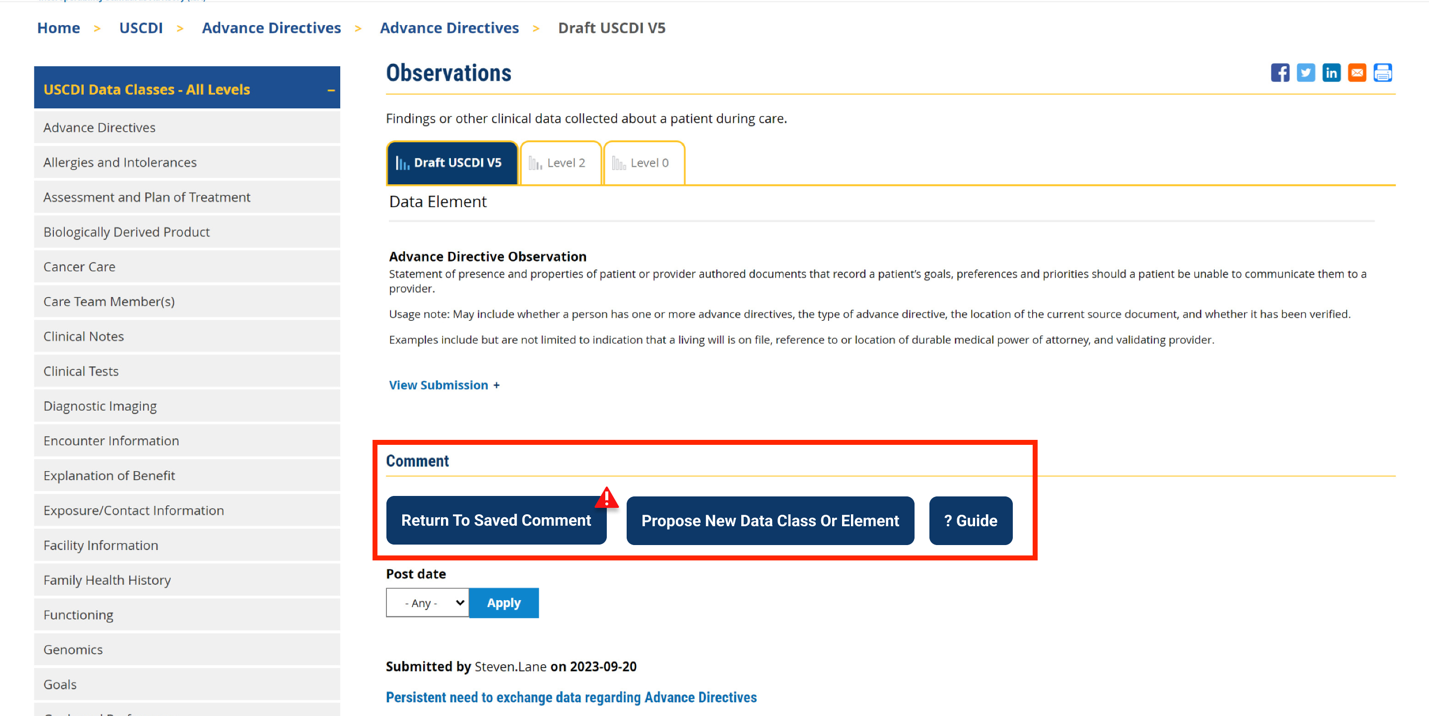
Instead of clicking the "Comment On An Existing Data Class Or Element" button, click the adjacent button labeled "Propose a New Data Class or Data Element."
This will redirect you to the ONDEC (ONC New Data Element and Class) Submission System.
In the ONDEC system, follow the provided instructions to submit your proposal for a new data class or element.
Once your proposal is submitted through ONDEC, it will be reviewed separately from the commenting process.
Fig 2 The "Propose a New Data Class or Data Element" button redirects users to the ONDEC Submission System for proposing new data elements not currently available in the system.
5. Complete the Comment Form
Fill out the required fields in the comment form:
Subject: Enter a brief, descriptive title that summarizes your comment. This helps reviewers quickly understand the nature of your feedback.
Comment: In this field, provide the full details of your comment or feedback. Be as clear and specific as possible about your suggestions, concerns, or observations. Include any relevant details that support your position.
6. Optional: Add Additional Comments
If you need to comment on multiple data classes or elements:
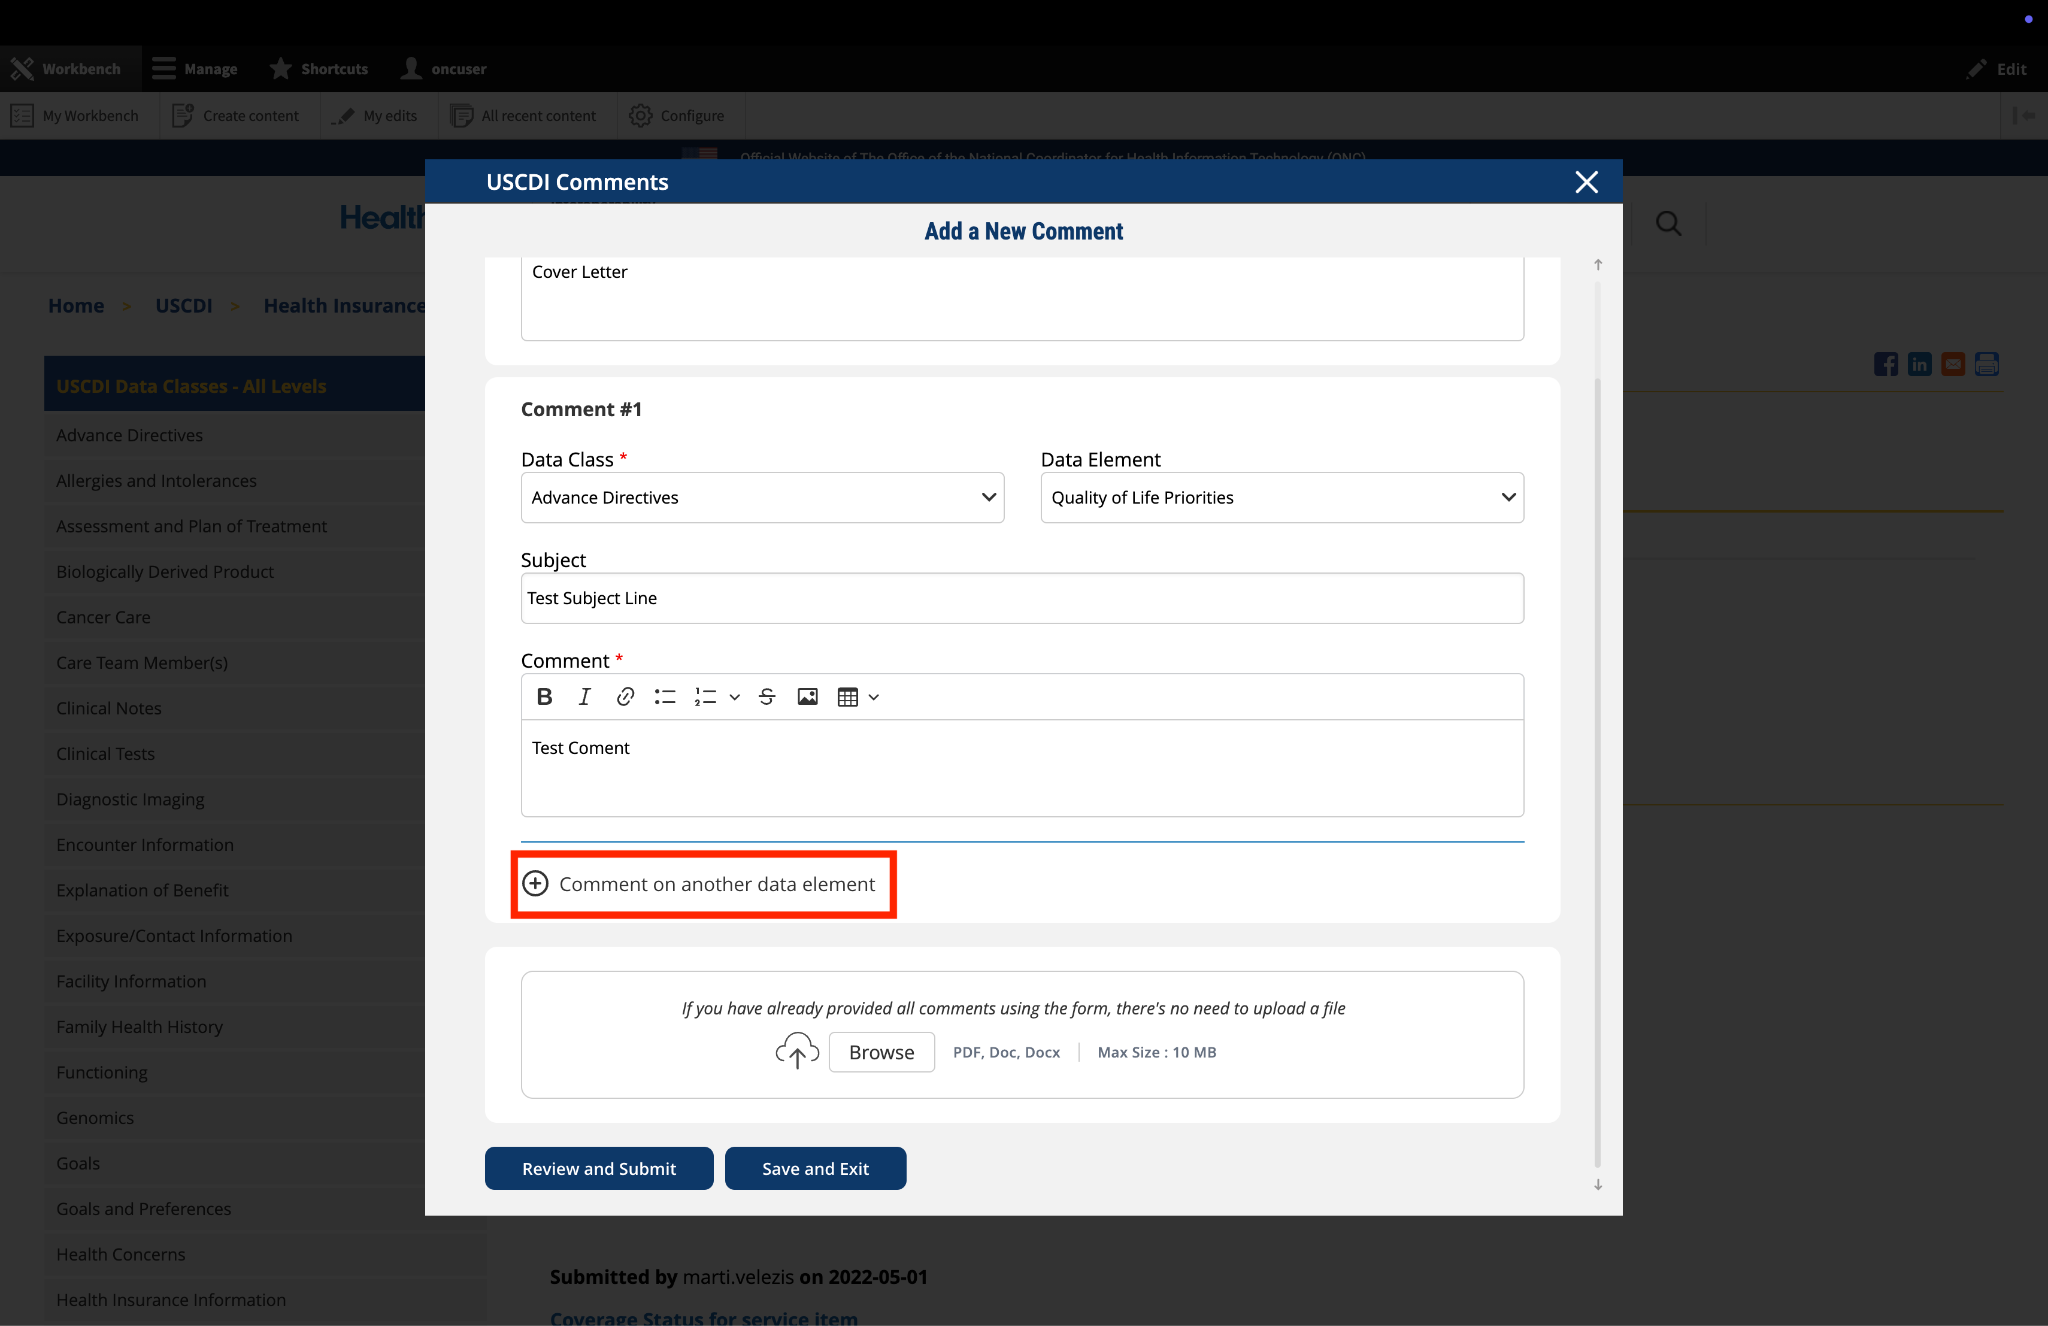
After completing your first comment, click the link labeled "Comment on another data element" at the bottom of the form.
A new comment section will appear, allowing you to enter details for your additional comment.
For each additional comment, you must select the appropriate data class and data element from the drop-down menus.
Complete the Subject and Comment fields for your additional comment.
Repeat this process for each additional comment you wish to submit.
Fig 3 The "Comment on another data element" link enables users to create multiple comments addressing different elements within a single submission.
7. Optional: Upload Supporting Files
The platform allows you to upload supporting documentation to enhance your comment:
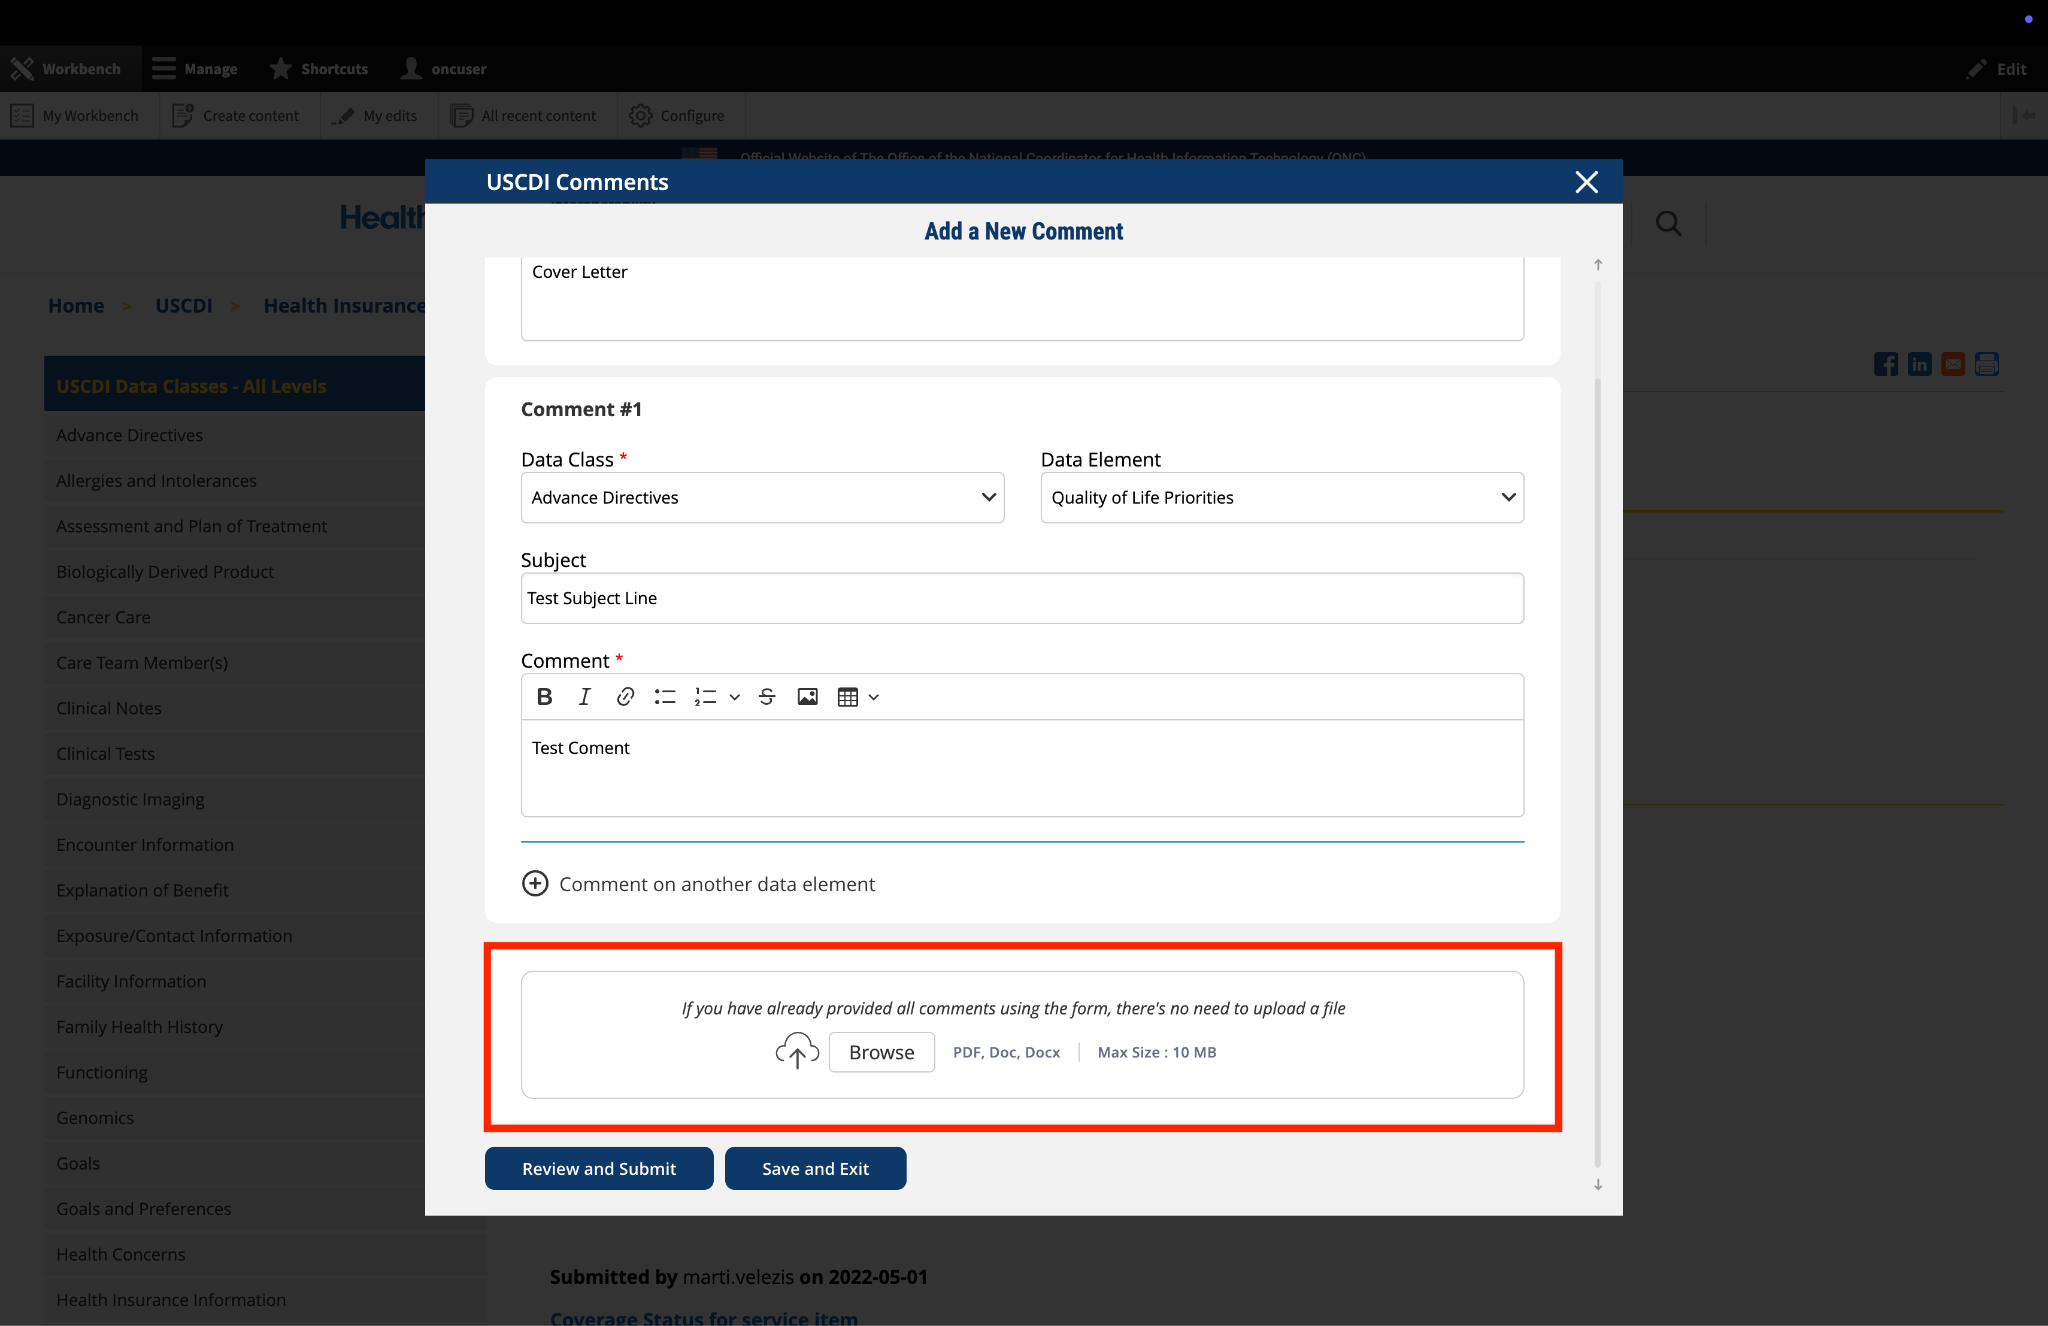
Locate the "File Upload" section at the bottom of the comment form.
Click to upload any files (such as PDFs or documents) that provide additional context, evidence, or clarification for your comment.
Important: If you have already entered your comments using the form fields, there is no need to upload duplicate content in PDF format. The file upload feature is intended for supplementary materials only. Please avoid uploading files that contain the same information already provided in your comment text.
Fig 4 The "File Upload" section permits users to attach supporting documentation that supplements their written comments.
8. Optional: Save and Exit
If you need to pause your work and return to complete your comment later:
Click the "Save and Exit" button at the bottom of the form.
Your comment will be saved as a draft that you can access and complete later.
When you return to the platform, you will see a red triangle with an exclamation mark next to the “Return to saved Comment” button, indicating that you have saved comments in draft status.
Click this button to continue working on your draft.
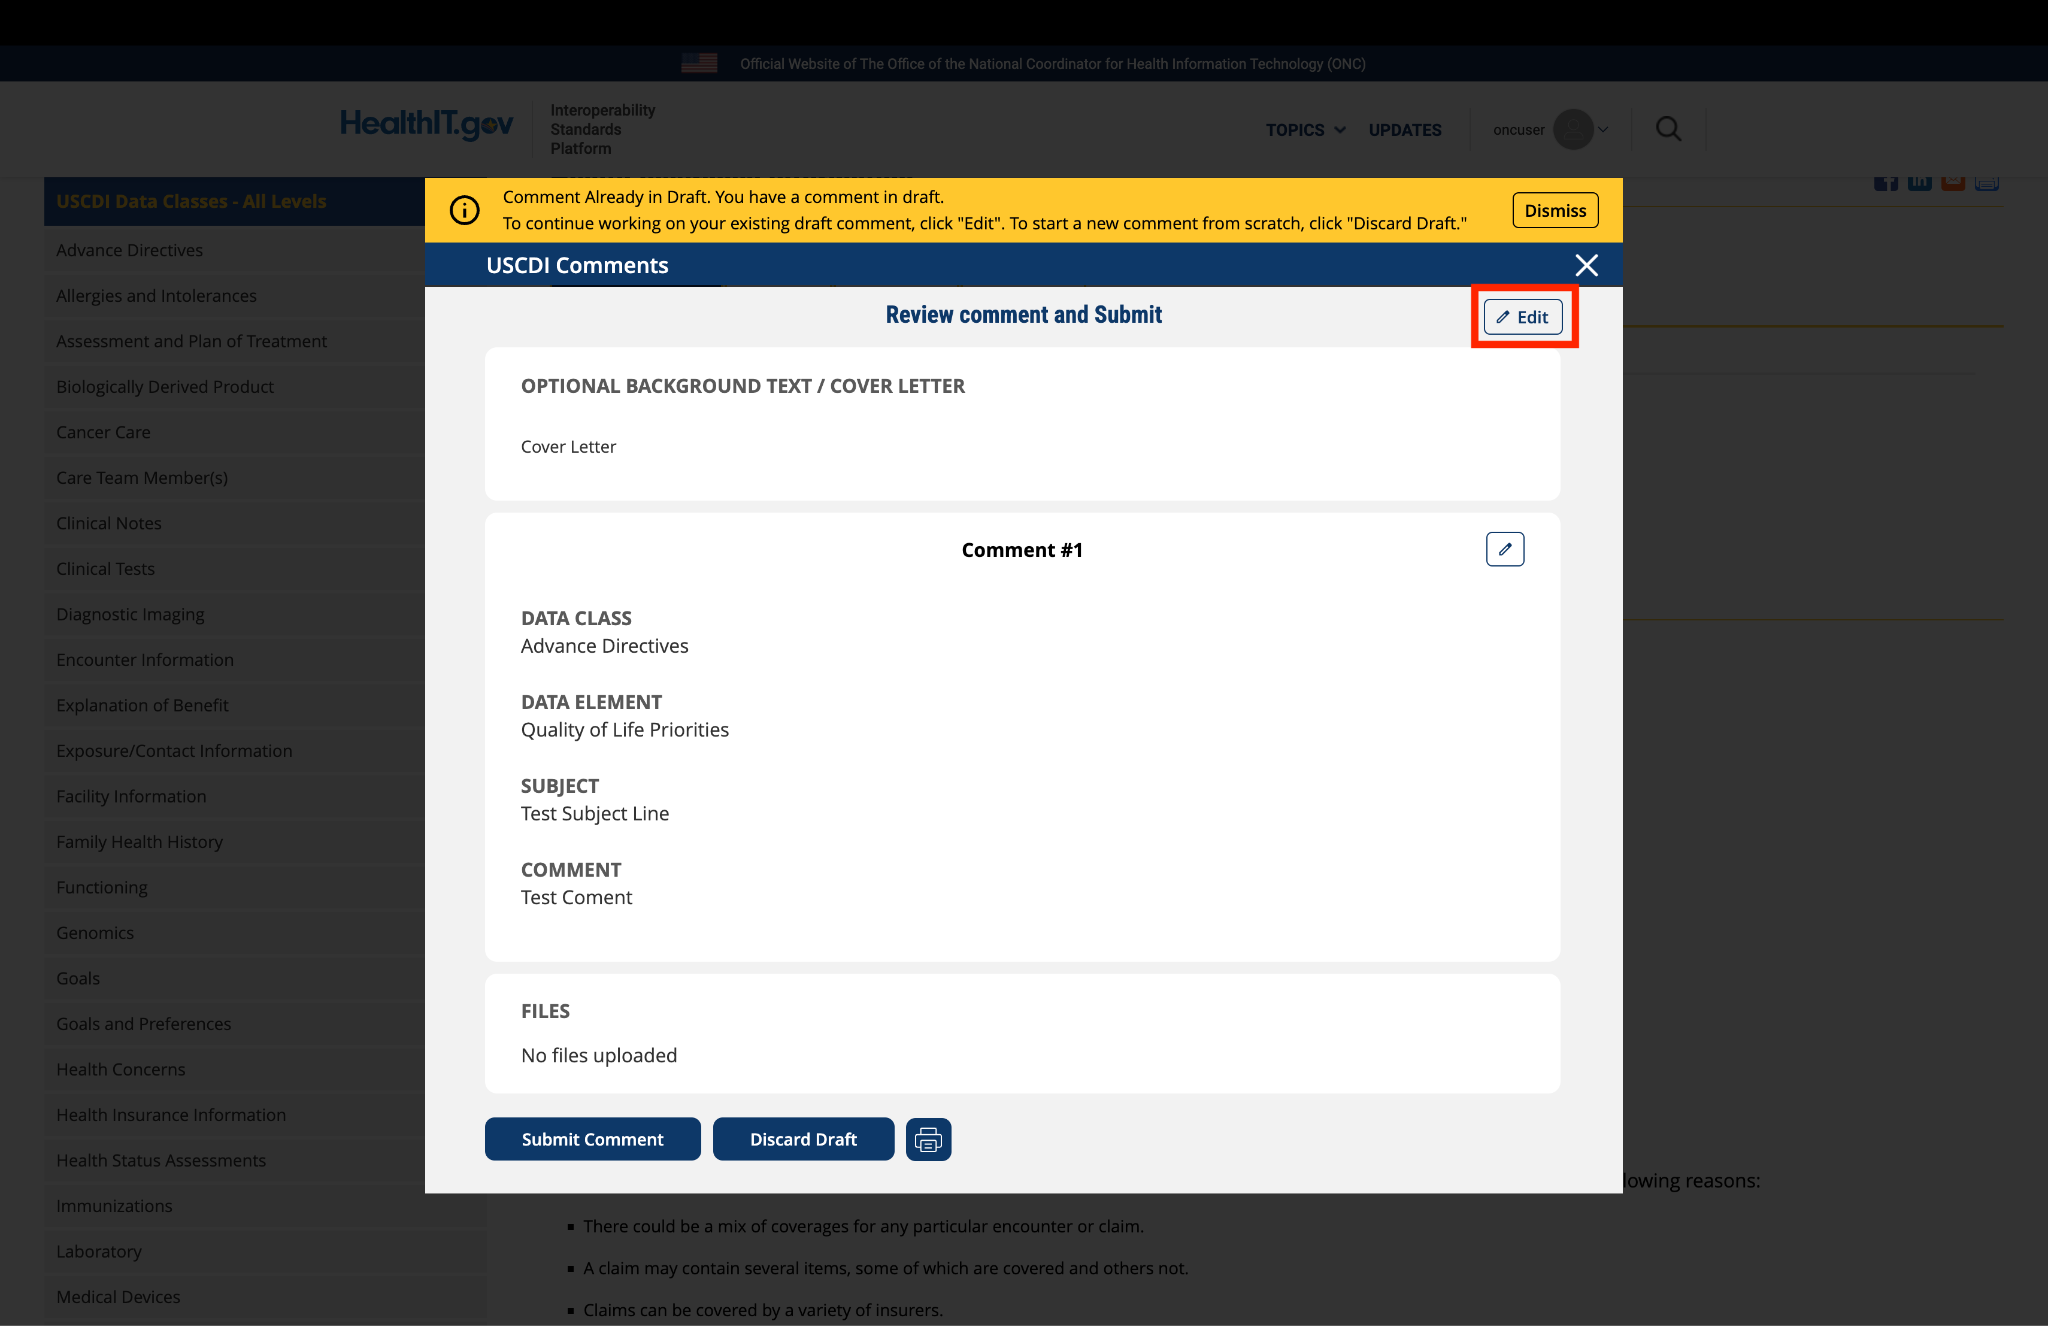
You will be taken to a review page where you can:
Select "Submit Comment" to officially submit your feedback.
Click "Edit" to return to the comment form and make changes
Select "Discard Draft" to delete the saved draft and start fresh
Fig 5 A red triangle with exclamation mark indicator appears next to the “Return to saved Comment” button when draft comments are saved in the system.
9. Review and Submit
Once you have completed your comment:
Click the "Review and Submit" button at the bottom of the form.
This will take you to a review screen displaying your comment(s) in full.
Review all information for accuracy and completeness.
On this review screen, you have three options:
Click "Submit Comment" to officially submit your feedback
Click "Edit" to return to the comment form and make changes
Click "Discard Draft" to delete the comment and start fresh
The review screen also includes a "Print" button that allows you to create a printed copy of your comments for your records.
If you choose to submit, your comment will be recorded in the system and made available for review by the appropriate stakeholders.
Fig 6 The review screen allows users to verify comment content and make any necessary modifications before final submission.


Submitted by claricelmiller… on
AOTA's Comment on Mental Function
The American Occupational Therapy Association supports and appreciates the inclusion of mental functions in the health status data class. AOTA participates in the PACIO Project work on the Cognitive Status Implementation Guide that has since been renamed to Functional Performance. Developing an interoperable and interdisciplinary method of collecting information on an individual's mental functions is crucial in early detection of cognitive decline, onset of delirium, or identification of trends over time. AOTA encourages ONC to consider how this data can be efficiently and accurately collected beyond admission and discharge and how data from other clinicians, such as occupational therapy practitioners, can be utilized in this data class.
2022 USCID Final Comments_2.pdf